
BMV — Catheter-Based Treatment for Mitral Stenosis
MV may widen a narrowed mitral valve in selected patients. Suitability depends on valve anatomy, condition severity and other clinical factors.



What is mitral stenosis?
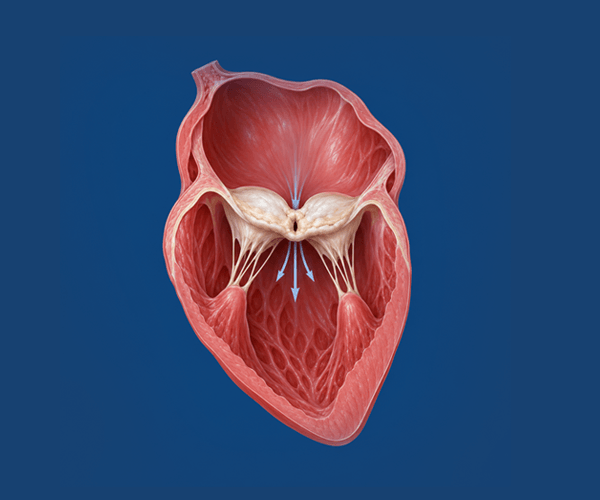
Mitral stenosis is a narrowing of the mitral valve that restricts blood flow from the left atrium to the left ventricle. In India, it is most commonly caused by rheumatic heart disease.
Narrowing can increase left atrial pressure and affect flow through the heart. Over time, this can cause symptoms — and Depending on severity, mitral stenosis may be associated with atrial fibrillation, pulmonary hypertension and heart failure
Common symptoms
- Breathlessness — on exertion, or when lying flat
- Fatigue and reduced exercise tolerance
- Palpitations, which may indicate atrial fibrillation
- Swelling of the legs or ankles
- In more advanced disease: coughing up blood (haemoptysis)
A proper medical evaluation — including echocardiography — is needed to confirm the diagnosis and determine severity.
What is Balloon Mitral Valvotomy?
BMV/PTMC is a catheter-based intervention used in selected patients with mitral stenosis.
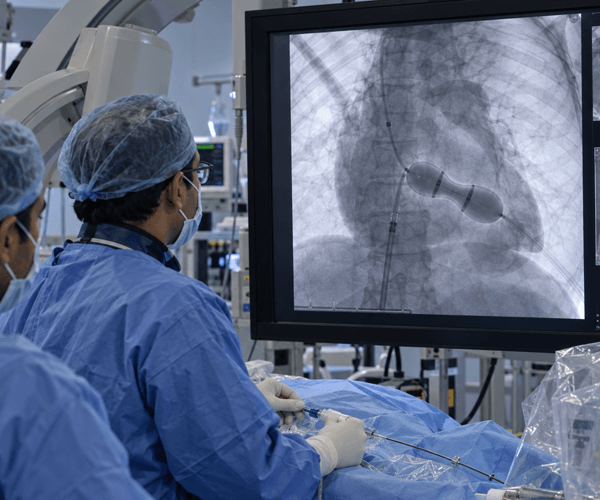
A thin, flexible Catheter usually enters through a vein in the groin and is guided into the heart. Balloon helps separate fused mitral valve commissures. The procedure aims to improve valve opening and blood flow; the result varies.
Success rates apply to carefully selected patients with suitable valve anatomy. Individual outcomes vary. Source: ACC/AHA Valvular Heart Disease Guidelines; published BMV outcome data.
Who May Be Considered for BMV?
BMV may suit selected patients with favourable anatomy for balloon commissurotomy. A detailed echocardiogram — and sometimes a transoesophageal echo — is used to assess suitability.






BMV is not suitable for every patient with mitral stenosis. Choices may include observation, medication, commissurotomy or surgery; multidisciplinary review where appropriate.
How BMV is performed
BMV is carried out in a cardiac catheterisation laboratory under fluoroscopic and echocardiographic guidance. It is a planned procedure, sedation/anaesthesia selected according to the clinical and imaging requirements.




Published Clinical Evidence on BMV
In appropriately selected patients, Published studies evaluate valve function, symptoms, complications and follow-up in selected patients. The data below reflects outcomes at specialist centres in carefully selected patients — individual results vary.
Sources: Published BMV/PTMC outcome data; ACC/AHA Guidelines for the Management of Patients with Valvular Heart Disease; Iung B et al., European Heart Journal. These figures represent outcomes in selected patient cohorts and should not be interpreted as individual expected outcomes. All patients are assessed individually by the Heart Team before any recommendation is made.

Recovery after BMV
Recovery after catheter-based BMV may differ from surgery; course varies. The exact timeline depends on each patient's overall health and how the heart responds.
Monitoring After the Procedure
- Monitoring of heart rhythm, blood pressure and access site
- Echocardiogram before discharge to assess valve result
- Mobilisation depends on stability, vascular access management and medical advice.
- Anticoagulation is reviewed — may continue if atrial fibrillation is present
After discharge
- Return to daily activity depends on recovery and medical advice.
- Echocardiography according to clinical findings and follow-up plan.
- Review medication according to rhythm, thromboembolic risk and other indications.
- Regular cardiac review is important: BMV may not be permanent in all patients
Potential Risks and Long-Term Considerations
As with all cardiac catheter procedures, BMV carries risk. The exact risks depend on individual patient health, valve anatomy and the clinical context. Individual risks, benefits and alternatives should be discussed for informed consent.
Procedure-related risks
- New or worsening leakage is an important complication.
- Cardiac perforation or tamponade may occur.
- Stroke/systemic embolism may occur - screening helps but cannot eliminate risk.
- Need for emergency cardiac surgery
- Access-site complications (bleeding, bruising)
Longer-term considerations
- Restenosis may develop- timing and further care vary.
- AF may persist and medication depends on clinical indications.
- Ongoing follow-up is important to monitor valve function and symptom status
Frequently asked questions
BMV is a catheter-based intervention used for selected patients with mitral stenosis. Surgical options may include commissurotomy, repair or replacement according to the valve and overall condition. Each approach has different indications, benefits, risks and limitations.
BMV does not necessarily provide a permanent result. The valve can narrow again; the likelihood and timing depend on anatomy, age, procedural result and other factors. Clinical review and echocardiography help monitor valve function. Some patients need further treatment.
BMV may be unsuitable with significant pre-existing regurgitation, left atrial thrombus or unfavourable valve anatomy, including certain severe calcification or subvalvular patterns. Eligibility requires appropriate clinical investigation.
Evaluation includes clinical review and transthoracic echocardiography. TEE may be used to assess thrombus and valve anatomy; ECG, blood tests or other investigations may be needed.
Duration varies by anatomy, procedure complexity, anaesthesia and clinical factors. Preparation and monitoring add time beyond the procedure; the treating team should explain anticipated requirements